
by Dr. Loni Rodriguez | Dec 11, 2018 | Exercise advice, Injury Prevention, Running, running help, strength training
Why should runners strength train? PART I

The following is a very brief overview of Chris Johnson’s book, Running on Resistance. For more information about Chris and some of the amazing content he has to offer, visit his website at Chris Johnson PT.
Strength training is an integral part of any regular exercise routine. Here are some major benefits of this fundamental practice:
- Builds cardiovascular health
- Improves body image
- Improves flexibility
- Improves full body resiliency and resistance to injury
For runners, not only are you focused on the above, but for more competitive runners, there is a focus on performance. There is an element of excitement when we improve our mile time or come back for a run feeling refreshed.
Here are some of the running specific benefits that strength training can provide:
- Improve capacity
- Increase running economy
- Increase speed
- Delay fatigue onset
Body weight exercises are a great entry into resistance training, yet additional resistance with the use of weighted equipment will provide the necessary stimulus to gain strength. However, to reduce the risk of injury from strength training, a general periodization program should be followed. There are various programs out there and have been proven to be effective. The major areas of interest when choosing a program are exercise selection, recommendations for load, repetition count, and rest periods. Each of these should be well understood and planned before initiating a program.
Here are some general recommendations
- Exercises need to be individualized to the person’s goals and exercise history
- Initially, 2-3 sets of 8-12 reps of bodyweight movement. Progressed then to weighted routine as form and comfort improves
- Single leg exercises need little to no rest
- Two-legged exercises require a rest of 1-2 minutes recommended
- Frequency is most effective at about two days per week for 12 weeks on days of lower volume running or drill/tempo days
Stay tuned for Part II, where I will review the most important and effective exercises for runners to add into their regular routine.
WANT MORE?!?!?!?!?
Interested in live group training that covers this content?
We will be hosting a 3-part series workshop held on 3 consecutive Wednesday’s in January from 6:30-7:30pm
JANUARY 9th, 16th, and 23rd.
This workshop will be located at our brand new office on 1 Derby Street in Hingham. Space is limited so please sign up ASAP!
Email Loni through loni@infinitepotentialptw.com or call 617-249-4011 x 700 for ANY and all questions!
Sign up through this link– choose the 6:30pm class on January 9th. Follow the prompts to complete registration.

Are you interested in personalized programming?
It is a great way to safely and effectively implement this strength training program that was touched upon in the workshop.
HINT >>>> Most of it will be addressed in more detail in the 3-part series in January!
However, for a more personalized approach, the remote programming is a great way to be sure that you are doing EVERYTHING you need to do to improve your running performance and reduce your injury risk.
Email Loni through loni@infinitepotentialptw.com or call 617-249-4011 x 700 for ANY and all questions!


by Dr. Loni Rodriguez | Nov 19, 2018 | Back Pain, Exercise advice, Injury, Injury Prevention, knee pain, lifts, squats, working with injury
What to do when you are having pain during a workout?
Have you ever just left the gym or class when pain starts to occur? How annoying is that?! First off, you didn’t get a workout in, second, you might have hurt yourself… I hope not, and third, what do you do now? Should you go back to the gym tomorrow? Take a week off?
I really would like this post to come across the right way. I am by no means, telling you it is okay to push through any significant pain while exercising. What I would like to do is to provide a guideline of what to do when pain comes on during a workout.
Before I get into the guideline, there is one major exception:
*If you actually feel like you had an injury, as in, there was an EVENT that caused your pain, please stop exercising and seek medical attention*
Eg.
- if you fall off the treadmill, and feel a pop or snap in a joint followed by severe pain
- if you hit your head
- if something occurs and you notice immediate swelling and pain
…you get the point
What this guideline is NOT…
- A way to treat your pain
- A way to continue to exercise multiple sessions in a row without seeing guidance from a medical provider
- A way to avoid formally dealing with your injury
Point being… please seek medical advice to really help your issue!
In the meantime, I want you to be able to have some understanding of how to allow training to continue despite some pain vs taking time off.
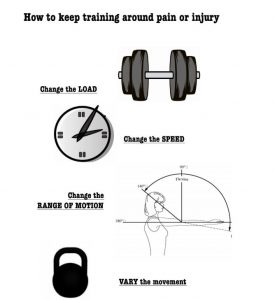
First… reduce the weight
- Try using a lighter weight, but continue the movement as prescribed.
- If the reps continue to be painful…
Next… slow it down
- Keep the weight and try using performing the movement slowly.
- If the reps continue to be painful…
Next… change the range of motion
- Keep the weight, return to a normal speed and limit how far you go into the movement being performed.
Finally… vary the movement
- There are various ways to perform different exercises.
- You can continue to get the same training effect while performing the movement in a slightly different way.
Here are a few examples of how you can vary the workout if you are experiencing pain during specific movements:
Knee pain with squatting?
- Reduce the load
- Alter the tempo – 3 seconds down, 3 seconds up
- Reduce the range of motion – Squat to a box or a bench
- Change the movement – go from front squats or goblet squats to a back squat
Back pain with deadlifting?
- Reduce the load
- Alter the tempo – try a quick lift from the floor and a slow lower
- Reduce the range of motion – Lift from an elevated surface (blocks or plates)
- Change the movement – go from a barbell to a hex bar or kettlebell
Use this to help keep yourself training, but PLEASE… also seek medical advice. There are many other things to be done in order to get you back to being pain-free during workouts… most of the time, it’s more exercise! Not rest.

by Dr. Loni Rodriguez | Nov 12, 2018 | Exercise advice, Injury, Injury Prevention
Should you exercise through injury?

I get asked many times about continuing to exercise despite being injured. This is definitely a loaded question. If you want to know how hard you can push yourself while dealing with pain, that concept is beyond the content in this post.
Today’s post is about what to do when you perform full body exercise on a regular basis and go and break your arm.
I would like to quickly highlight the inspiration of this post today- coach, teammate and friend, Miss. Adrienne Itri. This girl can not catch a break! She has been prepping for months for a competition this past weekend, training harder than ever and feeling the healthiest she has in a long time. She got there and gave it her all in event 1..… and broke her elbow. It was a fluke accident and could have happened to any of us. She is quite a trooper and a team player, however, showing up at the competition later that afternoon (following her trip to the hospital) AND the next day to cheer us on. No better teammate than that!
Hats off to you my good friend, I will help you every step of the way in this healing process!
Back to the post… I will be listing a few tips about the benefits of exercising around injury!
First piece of advice is… There is hope!
The good thing about functional fitness, is that there is a plethora of modifications that can be made to any exercise routine. These modifications can continue to allow for stimulation of muscle growth and improvements in endurance.
You won’t be doing exactly what you did before, but it will be damn near close.
Second, general exercise stimulate healing…
When you have an area of your body that needs some time to heal, it needs just that, time to heal. However, if you allow the other working parts of your body to exercise, you can stimulate the healing process of the injured region. It works through hormonal, heart rate and blood pressure stimulation.
Third, train the non-injured extremity…
There is a ton of research that shows strengthening the non-injured side can actually improve the strength of the injured side. In Adrienne’s case, she will be instructed to continue to perform as much strength training as she can using her right arm. Sure, the left arm will continue to have strength loss, however, training the right side will actually deaden the impact of not using her left arm for the next 6 weeks.

Fourth and final…
We all know that we FEEL better when we exercise. It increases endorphins, or your “feel good” hormones. If we are down and out because of a broken arm, we will feel even worse if we stay home and do nothing. So, if you are injured, please seek some advice from a trained professional who understands your injury and can help you create a modified program for the next few weeks of recovery!

by Dr. Loni Rodriguez | Sep 24, 2018 | Back Pain
 Why squatting and deadlifting are GOOD for your back.
People in pain have many beliefs about their symptoms in regards to why it is present, what is causing it, what could be contributing to the pain, etc. Specific to the topic of lifting, many feel that lifting or carrying heavily weighted objects or performing heavily weighted exercise can cause low back pain. Can you strain a muscle by lifting something? Of course! However, when performed properly, a regimen of free weight-based resistance training can actually help decrease these symptoms. I stumbled across a great article that I will break down into lay terms to help explain the importance of this type of resistance in people with low back pain.
Exercise has been recommended as the most effective conservative management for persistent low back pain in combination with addressing psychological, social, genetic and physical factors. There is evidence that resistance training, specifically, can help to eliminate the requirement for surgery or injections and can help reduce the related fear associated with low back pain. It has also been shown to be more effective at addressing low back pain compared to aerobic, coordination, Pilates, or mobilization training.
When looking at different types of resistance training, we think of machine-based and free-weights. Free-weight specific resistance training helps recruit the erector spinae and other posterior chain musculature which are very important in the treatment of low back pain. An in-depth discussion of free-weight vs. machine-based exercises is outside the scope of this post, however, the focus of the following resistance training program is based upon free-weight exercise. Participation in this type of training may be contrary to popular belief about what may be detrimental to a person experiencing low back pain.
A few factors that were looked at in this study were peoples compensatory movement patterns due to pain, the amount of fatty-infiltrated muscles of the lower back, lower back muscular endurance, pain levels, quality of life, and perceived level of disability. Compensatory movement patterns are seen in people with low back pain as they try and avoid movements of the lumbar spine. Specifically movements going from sitting to standing and bending forward to pick something from the ground are often guarded. This guarding and co-contracting of trunk musculature is an altered motor pattern that can enhance the disuse of spine musculature prolong the pain continuum. With the disuse of these muscles, fatty-infiltration and decreased muscular surface area can be seen and has been proven to be associated with people dealing with persistent low back pain.
The specific movements performed in this study were based around the squat and the deadlift, two movements that are functionally performed daily by all humans. A deadlift is simply picking something up from the ground and a squat is sitting down and standing up. The participants that were included were of ages 16-60, both men and women, having a history of low back pain for >3 months. They went through a 16-week program that consisted of 3 training days per week. The resistance training was based around 7-10 rep maximum which can be associated with moderate to heavy weight training (for the purposes of this article, specifics about the positive effects of loading with heavier weight training will not be discussed).
Results? Dramatic.
Significant decrease in fatty infiltration and increase in lumbar paraspinal muscle endurance without specifically training lumbar extension – basically meaning that the resistance training performed improved spine muscle quality and strength without directly training the spine muscles. The resistance training that was performed engaged the low back muscles in an effective way!
Pain, disability and quality of life were significantly improved by over 70%!
Body mechanics and coordination of the sit to stand (squat) movement were significantly improved with decreased presence of guarding.

Take home points?
- Including free-weight-based resistance training in a rehabilitation program could improve the outcome of the treatment.
- Try not to be afraid to lift weights! As long as it is done properly, a regular strength training routine can be a very effective aspect of a rehabilitation program.
![Nociception]()
by Dr. Loni Rodriguez | Sep 17, 2018 | Back Pain
 Nociception… what is it and why should you care?
Inside our bodies, we have these receptors (nociceptors) that sense movement, chemical and temperature changes. Why is this important? Because they tell us what is happening with our bodies and can be a very integral piece to explaining your current level of pain.
When changes in temperature, pressure, or movement are sensed, the receptors send signals to the spinal cord and up to the brain. The brain then gets to determine if it is a potential threat or not and take action. For example, if you place your hand near a hot stove, the receptors sense the heat, send the signal to the spinal cord then up to the brain. The signal is processed as threatening, it is sent down from the brain to the spinal cord to the receptors and tell your arm to pull your hand away. This is a normal and accurate response. However, sometimes these signals get crossed.
You can think of the spinal cord as a switchboard operator and the brain as the boss. All incoming calls are screened by the operator based on what the boss says are important (threatening) or not, some calls go to the boss, some don’t. When the boss or brain says that all calls are very important, the switchboard operator can begin confusing the incoming calls that are normally just categorized as pressure or movement and categorize them as threatening and painful. We now begin to sense normal things like pressure as pain and threatening. Our bodies get better at thinking we need protection and improve our ability to feel pain. However, if we can re-wire some of those crossed lines, we can attempt to improve the brains understanding of the normal signals, like pressure, and not interpret them as pain.
This is an important concept to comprehend because it can help you understand the some of the reason behind your symptoms that you are feeling. Do you want to learn more about pain? Stay tuned for future blog posts or message me directly at loni@infinitepotentialptw.com.
Reference
Greg Lehman – Recovery Strategies Pain Guidebook. (greglehman.com)

by Dr. Loni Rodriguez | Sep 10, 2018 | Back Pain, Dry Needling, Injury Prevention
Where do you think your pain is coming from??
There are many questions that I ask people when they come in for their first session. One of the questions that has dramatically improved my ability to connect with a person is to ask them, “what do you think is happening…?” OR “where do you think the pain is coming from…?” This allows the person to open up and tell more of their story and gives them some control. When is the last time a doctor asked you what you thought was going on?
Are you in pain…? Where do you think it is coming from? Answer that question guided by the following:
- Was my pain caused by physical activity?
- Does physical activity actually make my pain worse?
- Will physical activity harm my (enter area of pain here)?
- Are you afraid to move because you may feel it could make the pain worse?
Do you think you have structural damage? In many cases, structural damage is not the cause of the pain and gradual physical activity is the best medicine. It is my job as a clinician to help educate, or sometimes de-educate the person. You may have heard from another practitioner, google, WebMD, that there is something structurally wrong with you. This can instill a fear and confirms your thoughts that those structural abnormalities are causing the pain.
Are you fearful of moving? Have you been told NOT to do something that you love to do? Do you feel that if you move you will make things worse and increase your pain? In many situations, moving is OKAY. I love giving people the freedom to move. Empowering people to take control of their movement, their everyday tasks, and their lives again is an amazing part of my job. There is a time and a place for rest post-injury to allow an area of the body to calm down. However, that time is very short and when pain persists, lack of movement can cause worsening of the condition.
If you are dealing with pain like this, please seek some ACCURATE education from a qualified practitioner. Please do not let someone increase your fears and heighten your anxiety. There is so much evidence to support movement, loading the body and regular activity to assist in the treatment of pain. This treatment, however, has to be done gradually and with the assist of a professional! The body is extremely resilient and can recover from the state that it is in. So, be positive and find a coach, a physical therapist who can assist you on this journey to improving your quality of life.
Reference
Fear avoidance beliefs questionnaire
by Dr. Loni Rodriguez | Sep 4, 2018 | Back Pain
Have you ever felt stiffness in your lower back? Have you ever thought about what it could be? It feels like bone on bone, tearing, ripping, and compressing structures. It feels like there is a vice around your back, right? It’s doesn’t let you bend over, or touch your toes, or put on your shoes. What if I told you that this feeling could be a sensation, a protective response, that it may not correlate with any actual biomechanical stiffness?
Many conditions such as arthritis, neck pain, and low back pain treatments are targeted around joint stiffness. Stiffness is a significant predictor of disability. The most prevalent condition treated of these three is low back pain, accounted in about 10% of individuals worldwide. As healthcare costs rise, our ability to treat this area does not improve, something is wrong here…
The following explains the findings of a 2016 study by Stanton et al, whom experimented to explain the argument against a correlation of actual structural stiffness and the perception of feeling stiff. They looked at structural stiffness, perception of force applied to the spine, and the effect of adding an auditory stimulus to applied pressure to the spine. They compared individuals with chronic back pain and the perception of stiffness to healthy individuals without low back pain.
First, stiffness in the lower back was shown to be poorly correlated with actual objective stiffness in the structures of this area. Instead, it can be more accurately viewed as a “perceptual inference that may serve to reduce movement and re-injury.” (1) Stiffness can be viewed as a possible learned behavior that severed to protect a once acutely injured area. Our bodies are extremely smart and they try and protect us from injury, however, once the injury has healed, if we do not retrain that area to move once again, it will remain guarded, “stiff” if you will.
Second, people with the perception of stiffness in their lower back overestimated the amount of force applied to the spine and were better at detecting a change in this force applied. Being hypersensitive in an area of the body can be correlated with a change in the brain’s perception of how it views, controls, and perceives that area. The connection is a bit blurry. With a blurry connection, the brain can get protective and hence can create this learned “stiffness”
Lastly, adding a sound in conjunction with the applied force altered the sensation of the degree of force applied to the area of the spine. This means when force was applied to the spine with a sound that is perceived as light, soft, airy, it changed how much force the person reported feeling.
This article concluded that the feeling of stiffness in the spine is multimodal and is derived from both sensory and perceptual inputs, NOT necessarily actual spine stiffness. This is a very interesting finding and can significantly alter how we as clinicians treat low back pain. As a person with low back pain, this can change how you view your symptom. It does not mean that it is not there, it is truly there! You feel the stiffness, but what this article debunks is the feeling that there is actual, structural stiffness that needs to be broken up, stretched, or cut. Next time you feel that symptom, try and think about what is NOT happening vs what you may think is happening.
Reference
Stanton et al. Feeling stiffness in the back: a protective perceptual inference in chronic low back pain. Scientific Reports August 29, 2017.

by Dr. Loni Rodriguez | Aug 27, 2018 | Back Pain

A patient’s imaging results are one of the most popular topics of conversation within the first 15 minutes of almost every evaluation with a new client experiencing low back pain. The client will either be questioning going for an MRI or be describing what was found when they received one in the past. I listen to them, I hear them out, then I drop the knowledge bomb on them…
The prevalence of an abnormal finding is high in people without symptoms and this increases with age. This means that most findings on images are normal and do not always correlate with pain. So, bulging discs, degenerative disc disease, and disc protrusions are like the gray hairs of the spine? Wrinkles on the inside? Pretty much.
A systematic review by Brinjikji et al went through articles that analyzed the imaging findings of 3110 asymptomatic individuals. The findings were outstanding:
- 30% of people at the age of 20 had disc bulges, this increased to 60% at age 50, and 84% at age 80.
- 23% of people at age 20 had disc protrusions and up to 43% at age 80
So, how relevant are the findings on MRI? Not always very relevant at all. This raises the discussion about how imaging findings impact the management of patients with low back pain. Is it very important for clinicians to know what a MRI will reveal? Imaging of the lumbar spine has not been shown to improve clinical outcomes. Why would we want to pay for a very expensive exam that will not change the course of care, management or outcome of treatment of low back pain? I know I sure wouldn’t.
Yet, I do empathize with patients wanting to “…just want to know what is going on inside.” However, what you must understand is that over half of 50 year olds imaged in the study discussed above, had a bulging disc and they did not have pain. Are you over 50? There is a high probability that you have one, too.
I do want to note that there are definitely circumstances when imaging is warranted. Images are necessary when we want to rule out red flag conditions such as cancer or fractures. So, before you jump to conclusions about what was found when you got that MRI, or push your doctor to order that image, remember that prevalence and relevance of abnormal findings are not synonymous. Pain is an experience that has sensory, cognitive and emotional components. What is found on the image is only a portion of what we as clinicians factor into the plan to help you feel better. Abnormal image findings and pain are not necessarily correlated and are likely part of the aging process.
Reference
Brinjikji et al. A Systematic Literature Review of Imaging Features of Spinal Degeneration in Asymptomatic Populations. American Journal of Radiology. 24 Nov 2014.
by Dr. Loni Rodriguez | Aug 21, 2018 | Back Pain

Recently, an article in the Boston Globe was brought to my attention by a patient of mine. It was in reference to opioid-related deaths in Massachusetts.
“The report by the Massachusetts Department of Public Health found that nearly a quarter of overdose deaths in a five-year period occurred among people, mostly men, who work in construction. Farmers and fishermen also had higher-than-average rates of overdose deaths.
The common factor: Workplace injuries occur frequently in these occupations.”
The current method of pain management has a very unfortunate cycle. The article referenced above gives a disturbing example of how the management of pain MUST change. Based on this article, we can assume that there may be a relationship with injury / pain and opioid addiction-related death. The image below describes popular pain management after being hurt on the job (or getting injured in any manner):
Go to the doctor

Prescribed pain medication (Opioids in most cases)
Pain improves = more / continued medication
Reliance on Pain medication
Possible addiction… etc
What if there was existing treatment that has been proven to decrease the rate of opioid prescription?
A recent study published by Dr. Bianca Frogner discusses the effect of choosing Physical Therapy as the first line of defense to address low back pain. She reports that there was an 89.4% reduction in opioid addiction rates for patients who saw a PT to address their pain FIRST vs any other form of pain management. Health News from NPR published a great article that helps summarize Dr. Frogner’s study. This is a staggering number! Physical therapy has been shown to dramatically effect this epidemic if it is chosen as the first line of defense. If we can begin to raise awareness on this topic, can there be a shift from opioid prescription to physical therapy prescription? I sure hope so.
References
Frogner et al. “Physical Therapy as the First Point of Care to Treat Low Back Pain: An Instrumental Variables Approach to Estimate Impact on Opioid Prescription, Health Care Utilization, and Costs”. Health Serv Res. 2018 May 23.

by Dr. Loni Rodriguez | Aug 13, 2018 | Back Pain

Where the heck is my back pain coming from?
What I was taught in PT school was that back pain was mechanical. It was coming from a muscle imbalance, tight hamstrings, tissue damage, a weak core, an unstable lumbar spine, etc. This directed treatment around a biomedical approach.
However, over the last 10 years there has been a significant shift in the way that low back pain is treated and approached. Additionally, this shift has been more profoundly researched in the study of low back pain, specifically. This is the biopsychosocial model of addressing this epidemic. There has been an immense amount of research on the connection between low back pain and psychological factors, social factors, beliefs about pain, pain catastophization, poor nutrition, lack of sleep, and co-morbid conditions. These factors are affecting patients therapeutic outcome AND their risk of long-term disability. Low back pain goes far beyond tissue damage!
For example, a patient has a higher risk of developing low back pain if they are dealing with depression. Patients whom are living with excess stress about finances, losing their job, or poor work satisfaction are more likely to experience low back pain. These are some examples of the social and psychological factors that must be addressed within a treatment plan.
Beliefs about pain and pain catastrophization also have been shown to play a role in persistent low back pain. It has been shown that the brain observes the world around us and makes predictions about how things are going to feel. It adapts to what we become used to and mimics the thoughts, feelings and beliefs beginning at early childhood with the observation of our parents. Similar coping styles are observed in children that resemble those of the adult.
So, if you witnessed your mother or father deal with debilitating, persistent low back pain for the greater part of your childhood, you may be more likely to experience this level of debilitating pain.
We also respond to others in pain with neuropsychological reactions, including anxiety and distress. If you are to watch someone experience a horrific bout of back pain, you will then begin to have negative thoughts during any back pain that you may experience in the future. Similarly, responding in dramatic fashion to a current bout of back pain can truly make it worse!
One thing that I am NOT eluding to is that back pain is “all in your head”. There are absolute circumstances when a tissue overuse condition can occur and may be CONTRIBUTING to the symptoms, but the CAUSE and EFFECT is not black and white. Back pain is complex and 110% multi-factorial. All factors discussed above SHOULD be talked about and addressed to truly get to the root of the issue.
